Diabetes and Your Eyes: Retinopathy and Eye Health
Diabetes can affect the eyes in several ways, and diabetic eye disease often has no symptoms in its early stages. The encouraging news is that regular eye exams can catch problems early, when treatment works best, and keeping blood glucose, blood pressure, and cholesterol in range lowers the risk. This guide explains diabetic retinopathy and other eye conditions linked to diabetes, symptoms to watch for, screening, and treatment.
How diabetes affects the eyes
According to NIDDK, diabetic eye disease is a group of eye problems that can affect people with diabetes. These include diabetic retinopathy, diabetic macular edema, cataracts, and glaucoma. Over time, high blood glucose can damage the tiny blood vessels in the back of the eye. The CDC notes that diabetes is a leading cause of blindness in adults.
Diabetic retinopathy
The retina is the light-sensitive layer at the back of the eye that sends images to the brain. In diabetic retinopathy, damaged blood vessels in the retina may leak fluid or blood. The National Eye Institute (NEI) describes two main stages:
- Nonproliferative diabetic retinopathy (NPDR): The earlier stage. Blood vessel walls weaken, and small bulges may leak fluid and blood into the retina. Many people have no symptoms.
- Proliferative diabetic retinopathy (PDR): The advanced stage. The retina grows new, abnormal blood vessels. These fragile vessels can bleed into the gel in the center of the eye (vitreous), cause scar tissue, and lead to retinal detachment or glaucoma, which can cause serious vision loss.
Diabetic macular edema
The macula is the central part of the retina responsible for sharp, straight-ahead vision used for reading, driving, and recognizing faces. Diabetic macular edema (DME) occurs when fluid leaks into the macula and causes swelling, which blurs central vision. DME can happen at any stage of diabetic retinopathy.
Cataracts and glaucoma
NIDDK notes that people with diabetes are more likely to develop cataracts (clouding of the eye's lens) and to develop them at a younger age. Diabetes also raises the risk of some types of glaucoma, a group of diseases that damage the optic nerve. One type, neovascular glaucoma, can result from abnormal blood vessel growth caused by retinopathy.
Who is at risk?
Anyone with any type of diabetes, including gestational diabetes, can develop diabetic eye disease. The risk increases with:
- Longer duration of diabetes
- Blood glucose that stays above target
- High blood pressure
- High cholesterol
- Smoking
- Pregnancy in people who already have diabetes, which can make retinopathy worse; NEI notes that pregnant people with diabetes should have eye exams during pregnancy
Symptoms
Early diabetic eye disease usually has no symptoms. You can have good vision and still have damage. As it progresses, symptoms may include:
- Blurry or wavy vision
- Vision that changes often, sometimes from day to day
- Dark areas or vision loss
- Poor color vision
- Spots or dark strings floating in your vision (floaters)
- Flashes of light
Seek urgent eye care if you have sudden vision changes, many new floaters, flashes of light, or a curtain or shadow over part of your vision.
Note that blurry vision can also come from short-term changes in blood glucose, which affect the lens of the eye. This usually improves when glucose returns to target, but any persistent change should be checked.
Eye exams: the most important step
Because early damage has no symptoms, regular screening is essential. NEI and NIDDK recommend that people with diabetes get a dilated eye exam at least once a year, unless their eye care professional recommends a different schedule. The ADA's Standards of Care offer general timing guidance:
- Type 1 diabetes: A first dilated eye exam within five years of diagnosis.
- Type 2 diabetes: An exam soon after diagnosis, because damage may already be present.
- Ongoing: Usually yearly; your eye doctor may recommend every one to two years if there is no retinopathy and diabetes is well managed, or more often if retinopathy is present or worsening.
- Pregnancy: People with preexisting diabetes should have an eye exam before or early in pregnancy and follow-up as recommended.
What happens during a dilated eye exam
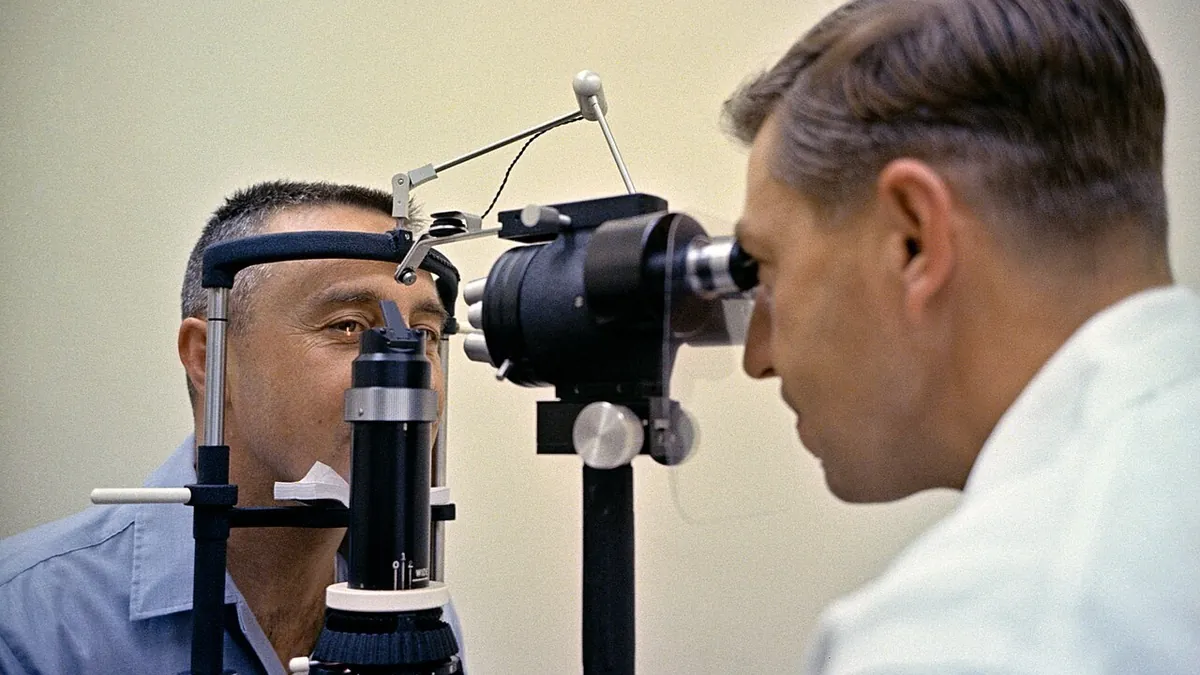
The eye care professional puts drops in your eyes to widen (dilate) the pupils, then examines the retina and optic nerve. Your vision may be blurry and sensitive to light for several hours, so bring sunglasses and consider arranging a ride. Other tests may include retinal photographs or optical coherence tomography (OCT), which creates detailed images of the retina. Some primary care offices use retinal cameras, sometimes with approved automated software, to screen for retinopathy and refer people who need further care.
Treatment
Treatment depends on the type and stage of eye disease. NEI describes several options:
- Anti-VEGF injections: Medicines injected into the eye that block a protein that promotes abnormal blood vessel growth and leakage. They are a common treatment for diabetic macular edema and can also treat proliferative retinopathy.
- Laser treatment: Laser can seal leaking blood vessels or shrink abnormal vessels.
- Steroid injections or implants: Can reduce swelling in the macula for some people.
- Vitrectomy: Surgery to remove blood or scar tissue from the vitreous gel.
- Cataract surgery: Replaces a cloudy lens with a clear artificial lens.
Early treatment can slow or stop progression and protect vision. Treatment does not cure diabetes, so ongoing exams and glucose management remain important.
Protecting your eyes
- Keep blood glucose near your target. See A1C and blood sugar targets.
- Control blood pressure and cholesterol. See heart health.
- Don't smoke.
- Be physically active as your provider advises. If you have advanced retinopathy, ask which activities are safe, since heavy lifting or straining may need to be avoided.
- Get your dilated eye exam on schedule and follow up on any recommended treatment.
- Tell your eye doctor about any vision changes promptly.
The American Diabetes Association offers additional information on eye complications.
Living with low vision
If diabetes has affected your vision, low vision services can help. These include magnifiers, special lighting, large-print or talking glucose meters, and training to adapt daily tasks. Ask your eye care professional for a referral.
Key takeaways
- Diabetic retinopathy and macular edema often have no early symptoms but can cause vision loss.
- People with diabetes should have a dilated eye exam at least yearly or as their eye doctor advises.
- Effective treatments include anti-VEGF injections, laser, and surgery, and they work best when started early.
- Managing glucose, blood pressure, and cholesterol and not smoking help protect your eyes.
Sources
Links to the sources cited above appear in the text. We rely on the Centers for Disease Control and Prevention (CDC), the National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK), and the American Diabetes Association (ADA).